Volume 9, Issue 4 (Journal of Clinical and Basic Research (JCBR) 2025)
jcbr 2025, 9(4): 23-26 |
Back to browse issues page


Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Moslemi B, Sepehri H, Khoshbin Khoshnazar A. Effect of head and neck radiotherapy on blood pressure and orthostatic hypotension in patient with head and neck cancer. jcbr 2025; 9 (4) :23-26
URL: http://jcbr.goums.ac.ir/article-1-536-en.html
URL: http://jcbr.goums.ac.ir/article-1-536-en.html


1- Student Research Committee, Golestan University of Medical Sciences, Gorgan, Iran
2- Neuroscience Research Center, Golestan University of Medical Sciences, Gorgan, Iran; Biomedical Research Institute, School of Medicine, Golestan University of Medical Sciences, Gorgan, Iran
3- Department of Biochemistry and Medical Physics, Faculty of Medicine, Golestan University of Medical Sciences, Gorgan, Iran ,khoshbin@goums.ac.ir
2- Neuroscience Research Center, Golestan University of Medical Sciences, Gorgan, Iran; Biomedical Research Institute, School of Medicine, Golestan University of Medical Sciences, Gorgan, Iran
3- Department of Biochemistry and Medical Physics, Faculty of Medicine, Golestan University of Medical Sciences, Gorgan, Iran ,
Full-Text [PDF 431 kb]
(655 Downloads)
| Abstract (HTML) (1382 Views)
Discussion
The present study aimed to investigate the effect of head and neck cancer (HNC) radiotherapy (RT) on blood pressure (BP) and orthostatic hypotension. This study was conducted on 25 Iranian patients, with ages ranging from 20 to 70 years and a mean age of 55.2 years. The types of cancers included oral cavity cancer (50%), pharyngeal cancer (30%), and laryngeal cancer (20%). This distribution reflects the comparative prevalence of cancer types in the studied population and aligns with the epidemiological patterns of HNC in Iran.
The results of the present study indicated that changes in BP during a 3-month treatment period are common adverse effects of RT in patients with HNC. Specifically, these changes manifested as drops in systolic and diastolic BP, as well as orthostatic hypotension. On average, these patients experienced a 9 mmHg decrease in systolic BP after 1 month and a 14 mmHg decrease after 3 months. Additionally, decreases of 5 mmHg and 7 mmHg in diastolic BP were observed at 1 and 3 months, respectively. As reported in this study, patients with higher baseline BP were more vulnerable to BP drops following treatment. This complication may be due to damage to the baroreflexes of the carotid arteries, consistent with findings from previous studies (5,17-21).
In general, patients showed a significant reduction in both systolic and diastolic BP after 3 months. Although this was recorded in older patients or those with underlying diseases, no significant correlation was found between these factors. There is limited statistical evidence to confirm a relationship between underlying diseases and orthostatic hypotension.
In a study published by Goyal et al., it was discussed that radiotherapy to the neck area in these patients results in a reduction in heart rate variability and damages cardiovascular reflexes during postural changes from lying down to standing, which can increase the risk of cardiovascular problems (3). Consistent with our findings, Leibowitz et al. showed that patients with HNC undergoing radiotherapy experience significant changes in blood pressure during treatment. In particular, a decrease in systolic and diastolic blood pressure was observed, indicating the impact of treatment on cardiovascular regulation (6). In another article published by Okoye et al., the effect of head and neck radiotherapy on blood pressure and orthostatic hypotension in patients with head and neck tumors was discussed. It was stated that patients with head and neck cancer who underwent neck radiotherapy showed a significant and sustained decrease in both systolic and diastolic blood pressure (15).
Knowing this can help in more precise monitoring of medications and their side effects. This also indicates that drug therapy, as well as radiotherapy, may affect the cardiovascular system. Furthermore, understanding that patients experience decreases in systolic and diastolic blood pressure allows for preparing equipment to prevent injuries caused by falls, weakness, dizziness, and physical harm that low blood pressure can cause in these patients. Additionally, these results suggest that such a notable decrease in blood pressure can affect the hormonal balance system, body fluid volume, and autonomic nervous system function, and knowing this can help in managing the overall condition of the patients. This blood pressure decrease can also contribute to the understanding that these patients may have cardiovascular problems alongside other issues.
Another important aspect is the medications and their effects, whether alternative drugs can replace current ones that not only have fewer side effects but also provide better improvement for these patients. Therefore, more studies can help achieve this important goal. However, the limitation of our study is that we did not incorporate patients with other types of cancer undergoing RT due to patient diversity, the short follow-up period (3 months), single-center design, and lack of direct autonomic function testing. Further studies should focus on more participants and also explore the underlying mechanisms.
Conclusion
The results of this study confirm that alterations in blood pressure (BP) are significant complications of radiotherapy (RT) for patients with head and neck cancer (HNC). A larger cumulative dose of RT results in a more significant reduction in systolic BP. Additionally, as the total dose increases, the likelihood of experiencing orthostatic hypotension also rises. Furthermore, the longer the treatment duration, the more significant the average reduction in BP among patients. An increase in the total RT dose results in an elevated risk of orthostatic hypotension. Further studies could influence the treatment approach for these patients and may assist in guiding the use of medications that might alleviate this side effect.
Acknowledgement
The authors thank the Golestan University of Medical Sciences and Shafa Radiotherapy Center for their cooperation.
Funding sources
Golestan University of Medical Sciences, Gorgan, Iran, provided financial support for this study.
Ethical statement
This study was approved by the Ethics Committee of Golestan University of Medical Sciences with the approval code (Ethical code: IR.GOUMS.REC.1403.169).
Conflicts of interest
The authors declared no conflicts of interest.
Author contributions
This article is the result of a research project conducted in collaboration with Ms. Bahar Moslemi, Dr. Hamid Sepehri, and Dr. Alireza Khoshbin Khoshnazar at Golestan University of Medical Sciences.
Data availability statement
The data that support the findings of this study are available from the corresponding author upon reasonable request.
Full-Text: (862 Views)
Introduction
Head and neck cancer (HNC) is one of the most prevalent cancers globally and is a major cause of cancer-related deaths (1). Radiotherapy (RT) is crucial in the management of HNC, particularly in cases where the disease presents as regionally advanced. It can be employed as a primary therapeutic approach or in combination with surgical strategies, chemotherapy, or both. RT is a highly effective therapeutic method that improves survival outcomes and offers the potential for disease cure (2). The mechanism of RT involves the generation of cytotoxic free radicals within tissues exposed to radiation, leading to apoptosis and cell death, thereby targeting rapidly proliferating cancer cells. However, RT often causes collateral damage to surrounding normal tissues (3).
The adverse effects of RT are categorized based on their temporal onset, ranging from acute reactions occurring shortly after treatment to late effects that may manifest years post-therapy. Acute toxicities arise due to local inflammatory responses triggered by radiation and include painful mucositis, dysphagia, xerostomia, taste alterations, anorexia, and dermatitis. Chronic toxicities are primarily associated with fibrotic changes in tissues that have undergone prior inflammatory injury (2). Additionally, it has been reported that following neck irradiation, prolonged impairment frequently develops in the carotid arteries. Atherosclerotic and thrombotic complications have received significant attention (4-6). Chronic inflammation and fibrosis of the carotid artery walls may lead to "splinting" of the baroreceptors located in the carotid sinus. Since these receptors respond to stretch or deformation, increased rigidity of the carotid sinus is expected to result in impairment of the arterial baroreflex (3-9).
As patients age, they tend to develop comorbidities including hypertension, diabetes, and hyperlipidemia, which necessitate the use of antihypertensive medications due to the cardiovascular complications associated with these conditions. The immediate impact of neck radiotherapy on BP remains uncertain. There is a lack of data to assist physicians in addressing BP irregularities in these patients; therefore, numerous cardiovascular symptoms may be overlooked, potentially resulting in more severe complications (10-13).
As previously mentioned, the immediate effects of neck radiotherapy on BP are not clearly understood. Given the high global prevalence of head and neck tumors (14-16), the impact of HNC on BP regulation represents an important yet underexplored area of investigation.
Methods
Participants
In this study, 25 patients from the Shafa Radiotherapy Center of 5 Azar Hospital in Gorgan in 2024 participated (15 males and 10 females). All individuals were diagnosed with head and neck tumors. This study was approved by the ethics committee of Golestan University of Science (IR.GOUMS.REC.1403.169). Data from all qualifying patients referred to the center were gathered from hospital admission records and then analyzed. The ratio of males to females was roughly 3:1, which is consistent with the established epidemiology of head and neck cancers in Iran. The allocation of tumor locations among the participants was detailed as follows: oral cavity (50%), pharynx (30%), and larynx (20%), reflecting their relative frequency in the area. The eligibility requirements stipulated that participants must be a minimum of 18 years old and have provided written informed consent prior to their involvement.
Exclusion criteria
Patients who showed evidence of orthostatic hypotension prior to undergoing radiotherapy, as well as those with diabetic neuropathy and patients with Parkinson’s disease, were excluded from the study.
Experimental design
After obtaining informed consent and completing the necessary forms, each patient was provided with a form to collect demographic information, including age, gender, ethnicity, height, weight, and the presence of any underlying diseases. The Body Mass Index (BMI) was calculated based on the patient's height and weight. Blood pressure was measured in both sitting and standing positions using an appropriate blood pressure cuff during the first visit before the initiation of radiotherapy, one month after, and three months after the radiotherapy. Blood pressure was measured at two intervals of 5 minutes, and the average was recorded. Additionally, to assess postural blood pressure, the patient's pressure was measured after 5 minutes in the supine position, followed by measurements at 5-minute intervals in sitting and standing postures.
Statistical analysis
The data were entered into SPSS software version 27.0. Quantitative data were reported as mean and standard deviation, while qualitative data were presented in terms of abundance and frequency. After assessing the normalization of the data, chi-square or nonparametric tests were used to examine the Spearman’s correlation between variables. In this study, a significance level of 0.05 was considered.
Results
Hemodynamic assessment of patients
Assessment of systolic and diastolic BP
Before the RT intervention, the average systolic BP was 146 mmHg. After 1 and 3 months, it noticeably decreased to 137 mmHg and 132 mmHg, respectively. Initially, no patients experienced a fall in systolic BP. Five patients who initially had systolic hypertension experienced a drop in BP after a 3-month period, whereas only three patients without systolic hypertension experienced a drop in BP; the results indicate that this difference was significant. Initially, the patients' diastolic BP was reported as 86 mmHg, but over the 3-month period, this number decreased, and this reduction was numerically significant. Six of the patients who initially had high diastolic BP experienced a drop in BP after the 3-month treatment period, while only two of those who did not have high diastolic BP experienced a drop in BP, and this difference was statistically significant (P < 0.05, Figure 1).
Orthostatic hypotension
Patients with head and neck cancer were assessed for orthostatic hypotension three months after the initiation of radiation therapy. Orthostatic hypotension was experienced by 48% of the patients. The average age of these patients was 58.2 years, which did not differ significantly from the group without hypotension. Seventy-five percent of these patients had hypertension, three had hyperlipidemia, and four had diabetes. None of the patients with hypothyroidism experienced orthostatic hypotension (P > 0.05).
Effect of cumulative radiotherapy dose on BP
Spearman’s correlation test showed that higher cumulative radiation doses were associated with a greater drop in both systolic and diastolic BP, with effect sizes of 0.39 mmHg and 0.21 mmHg per Gy (Group level average changes), respectively. The decrease in systolic BP was statistically significant (P = 0.01). Patients receiving higher doses were also more vulnerable to orthostatic hypotension (Odds ratio 1.08 per Gy; 95% CI: 1.01 - 1.16). Among HNC patients receiving more than 70 Gy, 50% experienced orthostatic hypotension, compared to 52% in those receiving 70 Gy or less, and this difference was not statistically significant (P < 0.05).
Head and neck cancer (HNC) is one of the most prevalent cancers globally and is a major cause of cancer-related deaths (1). Radiotherapy (RT) is crucial in the management of HNC, particularly in cases where the disease presents as regionally advanced. It can be employed as a primary therapeutic approach or in combination with surgical strategies, chemotherapy, or both. RT is a highly effective therapeutic method that improves survival outcomes and offers the potential for disease cure (2). The mechanism of RT involves the generation of cytotoxic free radicals within tissues exposed to radiation, leading to apoptosis and cell death, thereby targeting rapidly proliferating cancer cells. However, RT often causes collateral damage to surrounding normal tissues (3).
The adverse effects of RT are categorized based on their temporal onset, ranging from acute reactions occurring shortly after treatment to late effects that may manifest years post-therapy. Acute toxicities arise due to local inflammatory responses triggered by radiation and include painful mucositis, dysphagia, xerostomia, taste alterations, anorexia, and dermatitis. Chronic toxicities are primarily associated with fibrotic changes in tissues that have undergone prior inflammatory injury (2). Additionally, it has been reported that following neck irradiation, prolonged impairment frequently develops in the carotid arteries. Atherosclerotic and thrombotic complications have received significant attention (4-6). Chronic inflammation and fibrosis of the carotid artery walls may lead to "splinting" of the baroreceptors located in the carotid sinus. Since these receptors respond to stretch or deformation, increased rigidity of the carotid sinus is expected to result in impairment of the arterial baroreflex (3-9).
As patients age, they tend to develop comorbidities including hypertension, diabetes, and hyperlipidemia, which necessitate the use of antihypertensive medications due to the cardiovascular complications associated with these conditions. The immediate impact of neck radiotherapy on BP remains uncertain. There is a lack of data to assist physicians in addressing BP irregularities in these patients; therefore, numerous cardiovascular symptoms may be overlooked, potentially resulting in more severe complications (10-13).
As previously mentioned, the immediate effects of neck radiotherapy on BP are not clearly understood. Given the high global prevalence of head and neck tumors (14-16), the impact of HNC on BP regulation represents an important yet underexplored area of investigation.
Methods
Participants
In this study, 25 patients from the Shafa Radiotherapy Center of 5 Azar Hospital in Gorgan in 2024 participated (15 males and 10 females). All individuals were diagnosed with head and neck tumors. This study was approved by the ethics committee of Golestan University of Science (IR.GOUMS.REC.1403.169). Data from all qualifying patients referred to the center were gathered from hospital admission records and then analyzed. The ratio of males to females was roughly 3:1, which is consistent with the established epidemiology of head and neck cancers in Iran. The allocation of tumor locations among the participants was detailed as follows: oral cavity (50%), pharynx (30%), and larynx (20%), reflecting their relative frequency in the area. The eligibility requirements stipulated that participants must be a minimum of 18 years old and have provided written informed consent prior to their involvement.
Exclusion criteria
Patients who showed evidence of orthostatic hypotension prior to undergoing radiotherapy, as well as those with diabetic neuropathy and patients with Parkinson’s disease, were excluded from the study.
Experimental design
After obtaining informed consent and completing the necessary forms, each patient was provided with a form to collect demographic information, including age, gender, ethnicity, height, weight, and the presence of any underlying diseases. The Body Mass Index (BMI) was calculated based on the patient's height and weight. Blood pressure was measured in both sitting and standing positions using an appropriate blood pressure cuff during the first visit before the initiation of radiotherapy, one month after, and three months after the radiotherapy. Blood pressure was measured at two intervals of 5 minutes, and the average was recorded. Additionally, to assess postural blood pressure, the patient's pressure was measured after 5 minutes in the supine position, followed by measurements at 5-minute intervals in sitting and standing postures.
Statistical analysis
The data were entered into SPSS software version 27.0. Quantitative data were reported as mean and standard deviation, while qualitative data were presented in terms of abundance and frequency. After assessing the normalization of the data, chi-square or nonparametric tests were used to examine the Spearman’s correlation between variables. In this study, a significance level of 0.05 was considered.
Results
Hemodynamic assessment of patients
Assessment of systolic and diastolic BP
Before the RT intervention, the average systolic BP was 146 mmHg. After 1 and 3 months, it noticeably decreased to 137 mmHg and 132 mmHg, respectively. Initially, no patients experienced a fall in systolic BP. Five patients who initially had systolic hypertension experienced a drop in BP after a 3-month period, whereas only three patients without systolic hypertension experienced a drop in BP; the results indicate that this difference was significant. Initially, the patients' diastolic BP was reported as 86 mmHg, but over the 3-month period, this number decreased, and this reduction was numerically significant. Six of the patients who initially had high diastolic BP experienced a drop in BP after the 3-month treatment period, while only two of those who did not have high diastolic BP experienced a drop in BP, and this difference was statistically significant (P < 0.05, Figure 1).
Orthostatic hypotension
Patients with head and neck cancer were assessed for orthostatic hypotension three months after the initiation of radiation therapy. Orthostatic hypotension was experienced by 48% of the patients. The average age of these patients was 58.2 years, which did not differ significantly from the group without hypotension. Seventy-five percent of these patients had hypertension, three had hyperlipidemia, and four had diabetes. None of the patients with hypothyroidism experienced orthostatic hypotension (P > 0.05).
Effect of cumulative radiotherapy dose on BP
Spearman’s correlation test showed that higher cumulative radiation doses were associated with a greater drop in both systolic and diastolic BP, with effect sizes of 0.39 mmHg and 0.21 mmHg per Gy (Group level average changes), respectively. The decrease in systolic BP was statistically significant (P = 0.01). Patients receiving higher doses were also more vulnerable to orthostatic hypotension (Odds ratio 1.08 per Gy; 95% CI: 1.01 - 1.16). Among HNC patients receiving more than 70 Gy, 50% experienced orthostatic hypotension, compared to 52% in those receiving 70 Gy or less, and this difference was not statistically significant (P < 0.05).
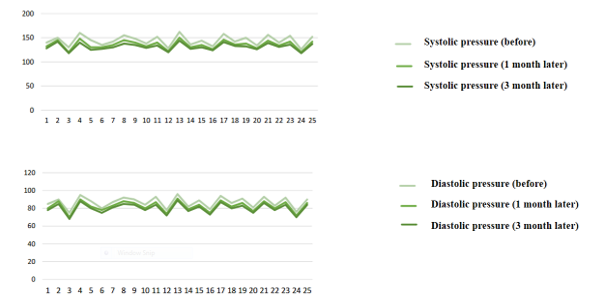 Figure 1. Line chart of systolic and diastolic BP levels in patients with head and neck cancer at intervals before radiotherapy, 1 month after, and 3 months after. The horizontal axis of the chart represents each test subject, and the vertical axis represents blood pressure. Data are presented as mean ± SD. |
Discussion
The present study aimed to investigate the effect of head and neck cancer (HNC) radiotherapy (RT) on blood pressure (BP) and orthostatic hypotension. This study was conducted on 25 Iranian patients, with ages ranging from 20 to 70 years and a mean age of 55.2 years. The types of cancers included oral cavity cancer (50%), pharyngeal cancer (30%), and laryngeal cancer (20%). This distribution reflects the comparative prevalence of cancer types in the studied population and aligns with the epidemiological patterns of HNC in Iran.
The results of the present study indicated that changes in BP during a 3-month treatment period are common adverse effects of RT in patients with HNC. Specifically, these changes manifested as drops in systolic and diastolic BP, as well as orthostatic hypotension. On average, these patients experienced a 9 mmHg decrease in systolic BP after 1 month and a 14 mmHg decrease after 3 months. Additionally, decreases of 5 mmHg and 7 mmHg in diastolic BP were observed at 1 and 3 months, respectively. As reported in this study, patients with higher baseline BP were more vulnerable to BP drops following treatment. This complication may be due to damage to the baroreflexes of the carotid arteries, consistent with findings from previous studies (5,17-21).
In general, patients showed a significant reduction in both systolic and diastolic BP after 3 months. Although this was recorded in older patients or those with underlying diseases, no significant correlation was found between these factors. There is limited statistical evidence to confirm a relationship between underlying diseases and orthostatic hypotension.
In a study published by Goyal et al., it was discussed that radiotherapy to the neck area in these patients results in a reduction in heart rate variability and damages cardiovascular reflexes during postural changes from lying down to standing, which can increase the risk of cardiovascular problems (3). Consistent with our findings, Leibowitz et al. showed that patients with HNC undergoing radiotherapy experience significant changes in blood pressure during treatment. In particular, a decrease in systolic and diastolic blood pressure was observed, indicating the impact of treatment on cardiovascular regulation (6). In another article published by Okoye et al., the effect of head and neck radiotherapy on blood pressure and orthostatic hypotension in patients with head and neck tumors was discussed. It was stated that patients with head and neck cancer who underwent neck radiotherapy showed a significant and sustained decrease in both systolic and diastolic blood pressure (15).
Knowing this can help in more precise monitoring of medications and their side effects. This also indicates that drug therapy, as well as radiotherapy, may affect the cardiovascular system. Furthermore, understanding that patients experience decreases in systolic and diastolic blood pressure allows for preparing equipment to prevent injuries caused by falls, weakness, dizziness, and physical harm that low blood pressure can cause in these patients. Additionally, these results suggest that such a notable decrease in blood pressure can affect the hormonal balance system, body fluid volume, and autonomic nervous system function, and knowing this can help in managing the overall condition of the patients. This blood pressure decrease can also contribute to the understanding that these patients may have cardiovascular problems alongside other issues.
Another important aspect is the medications and their effects, whether alternative drugs can replace current ones that not only have fewer side effects but also provide better improvement for these patients. Therefore, more studies can help achieve this important goal. However, the limitation of our study is that we did not incorporate patients with other types of cancer undergoing RT due to patient diversity, the short follow-up period (3 months), single-center design, and lack of direct autonomic function testing. Further studies should focus on more participants and also explore the underlying mechanisms.
Conclusion
The results of this study confirm that alterations in blood pressure (BP) are significant complications of radiotherapy (RT) for patients with head and neck cancer (HNC). A larger cumulative dose of RT results in a more significant reduction in systolic BP. Additionally, as the total dose increases, the likelihood of experiencing orthostatic hypotension also rises. Furthermore, the longer the treatment duration, the more significant the average reduction in BP among patients. An increase in the total RT dose results in an elevated risk of orthostatic hypotension. Further studies could influence the treatment approach for these patients and may assist in guiding the use of medications that might alleviate this side effect.
Acknowledgement
The authors thank the Golestan University of Medical Sciences and Shafa Radiotherapy Center for their cooperation.
Funding sources
Golestan University of Medical Sciences, Gorgan, Iran, provided financial support for this study.
Ethical statement
This study was approved by the Ethics Committee of Golestan University of Medical Sciences with the approval code (Ethical code: IR.GOUMS.REC.1403.169).
Conflicts of interest
The authors declared no conflicts of interest.
Author contributions
This article is the result of a research project conducted in collaboration with Ms. Bahar Moslemi, Dr. Hamid Sepehri, and Dr. Alireza Khoshbin Khoshnazar at Golestan University of Medical Sciences.
Data availability statement
The data that support the findings of this study are available from the corresponding author upon reasonable request.
Article Type: Research |
Subject:
Physiology
Received: 2025/11/29 | Accepted: 2025/12/25 | Published: 2026/06/9 | ePublished: 2026/06/9
Received: 2025/11/29 | Accepted: 2025/12/25 | Published: 2026/06/9 | ePublished: 2026/06/9
References
1. Pandit PN, Patil RA, Palwe VS, Tambade SH, Wagh SY, Gavit MK, et al. Patterns of blood pressure changes in patients with head and neck cancer receiving radiotherapy or chemo-radiotherapy at a tertiary cancer centre. Head Neck. 2021;43(4):1280-8. [View at Publisher] [DOI] [PMID] [Google Scholar]
2. Leibowitz A, Grossman E, Berkovitch A, Levartovski M, Appel S, Sharabi Y, et al. The Effect of Head and Neck Radiotherapy on Blood Pressure and Orthostatic Hypotension in Patients With Head and Neck Tumors. Am J Hypertens. 2018;31(2):235-9. [View at Publisher] [DOI] [PMID] [Google Scholar]
3. Goyal M, Shukla P, Gupta D, Bisht S, Verma NS, Tiwari S, et al. Cardiovascular sequel of neck irradiation in head and neck cancer patients. Int J Radiat Biol. 2017;93(7):711-6. [View at Publisher] [DOI] [PMID] [Google Scholar]
4. Sharabi Y, Dendi R, Holmes C, Goldstein DS. Baroreflex failure as a late sequela of neck irradiation. Hypertension. 2003;42(1):110-6. [View at Publisher] [DOI] [PMID] [Google Scholar]
5. Wang X, Hu C, Eisbruch A. Organ-sparing radiation therapy for head and neck cancer. Nat Rev Clin Oncol. 2011;8(11):639-48. [View at Publisher] [DOI] [PMID] [Google Scholar]
6. Bray F, Ferlay J, Soerjomataram I, Siegel RL, Torre LA, Jemal A. Global cancer statistics 2018: GLOBOCAN estimates of incidence and mortality worldwide for 36 cancers in 185 countries. CA Cancer J Clin. 2018;68(6):394-424. [View at Publisher] [DOI] [PMID] [Google Scholar]
7. GBD 2016 Mortality Collaborators. Global, regional, and national under-5 mortality, adult mortality, age-specific mortality, and life expectancy, 1970-2016: a systematic analysis for the Global Burden of Disease Study 2016. Lancet. 2017;390(10100):1084-150. [View at Publisher] [DOI] [PMID] [Google Scholar]
8. Pham TD, Teh M-T, Chatzopoulou D, Holmes S, Coulthard P. Artificial Intelligence in Head and Neck Cancer: Innovations, Applications, and Future Directions. Curr Oncol. 2024;31(9):5255-90. [View at Publisher] [DOI] [PMID] [Google Scholar]
9. Warnakulasuriya S, Chen THH. Areca Nut and Oral Cancer: Evidence from Studies Conducted in Humans. J Dent Res. 2022;101(10):1139-46. [View at Publisher] [DOI] [PMID] [Google Scholar]
10. Chow LQM. Head and Neck Cancer. N Engl J Med. 2020;382(1):60-72. [View at Publisher] [DOI] [PMID] [Google Scholar]
11. Martens T, Beck RW, Bailey R, Ruedy KJ, Calhoun P, Peters AL, et al. Effect of Continuous Glucose Monitoring on Glycemic Control in Patients With Type 2 Diabetes Treated With Basal Insulin: A Randomized Clinical Trial. JAMA. 2021;325(22):2262-72. [View at Publisher] [DOI] [PMID] [Google Scholar]
12. Sroussi HY, Epstein JB, Bensadoun R-J, Saunders DP, Lalla RV, Migliorati CA, et al. Common oral complications of head and neck cancer radiation therapy: mucositis, infections, saliva change, fibrosis, sensory dysfunctions, dental caries, periodontal disease, and osteoradionecrosis. Cancer Med. 2017;6(12):2918-31. [View at Publisher] [DOI] [PMID] [Google Scholar]
13. Kaufmann H, Norcliffe-Kaufmann L, Palma J-A. Baroreflex Dysfunction. N Engl J Med. 2020;382(2):163-78. [View at Publisher] [DOI] [PMID] [Google Scholar]
14. Norcliffe-Kaufmann L, Palma J-A. Blood pressure instability in head and neck cancer survivors. Clin Auton Res. 2020;30(4):291-3. [View at Publisher] [DOI] [PMID] [Google Scholar]
15. Okoye CC, Bucher J, Tatsuoka C, Parikh SA, Oliveira GH, Gibson MK, et al. Cardiovascular risk and prevention in patients with head and neck cancer treated with radiotherapy. Head Neck. 2017;39(3):527-32. [View at Publisher] [DOI] [PMID] [Google Scholar]
16. Huang C-C, Huang T-L, Hsu H-C, Chen H-C, Lin H-C, Chien C-Y, et al. Long-term effects of neck irradiation on cardiovascular autonomic function: a study in nasopharyngeal carcinoma patients after radiotherapy. Muscle Nerve. 2013;47(3):344-50. [View at Publisher] [DOI] [PubMed] [Google Scholar]
17. Koene RJ, Prizment AE, Blaes A, Konety SH. Shared Risk Factors in Cardiovascular Disease and Cancer. Circulation. 2016;133(11):1104-14. [View at Publisher] [DOI] [PMID] [Google Scholar]
18. Smith GL, Smith BD, Buchholz TA, Giordano SH, Garden AS, Woodward WA, et al. Cerebrovascular disease risk in older head and neck cancer patients after radiotherapy. J Clin Oncol. 2008;26(31):5119-25. [View at Publisher] [DOI] [PMID] [Google Scholar]
19. Baxi SS, Pinheiro LC, Patil SM, Pfister DG, Oeffinger KC, Elkin EB. Causes of death in long-term survivors of head and neck cancer. Cancer. 2014;120(10):1507-13. [View at Publisher] [DOI] [PMID] [Google Scholar]
20. Cooper JS, Pajak TF, Forastiere AA, Jacobs J, Campbell BH, Saxman SB, et al. Postoperative concurrent radiotherapy and chemotherapy for high-risk squamous-cell carcinoma of the head and neck. N Engl J Med. 2004;350(19):1937-44. [View at Publisher] [DOI] [PMID] [Google Scholar]
21. Clivio A, Fogliata A, Franzetti-Pellanda A, Nicolini G, Vanetti E, Wyttenbach R, et al. Volumetric-modulated arc radiotherapy for carcinomas of the anal canal: A treatment planning comparison with fixed field IMRT. Radiother Oncol. 2009;92(1):118-24. [View at Publisher] [DOI] [PMID] [Google Scholar]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |

This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International (CC BY-NC 4.0).
